This guide explains PMOC Abrava with an objective, clinician-focused overview of what it is, how it is planned, and what buyers typically evaluate when selecting products or services. Background information covers common clinical workflows, supplier considerations, and practical conditions for safe, consistent outcomes across dental-grade materials and treatment planning.
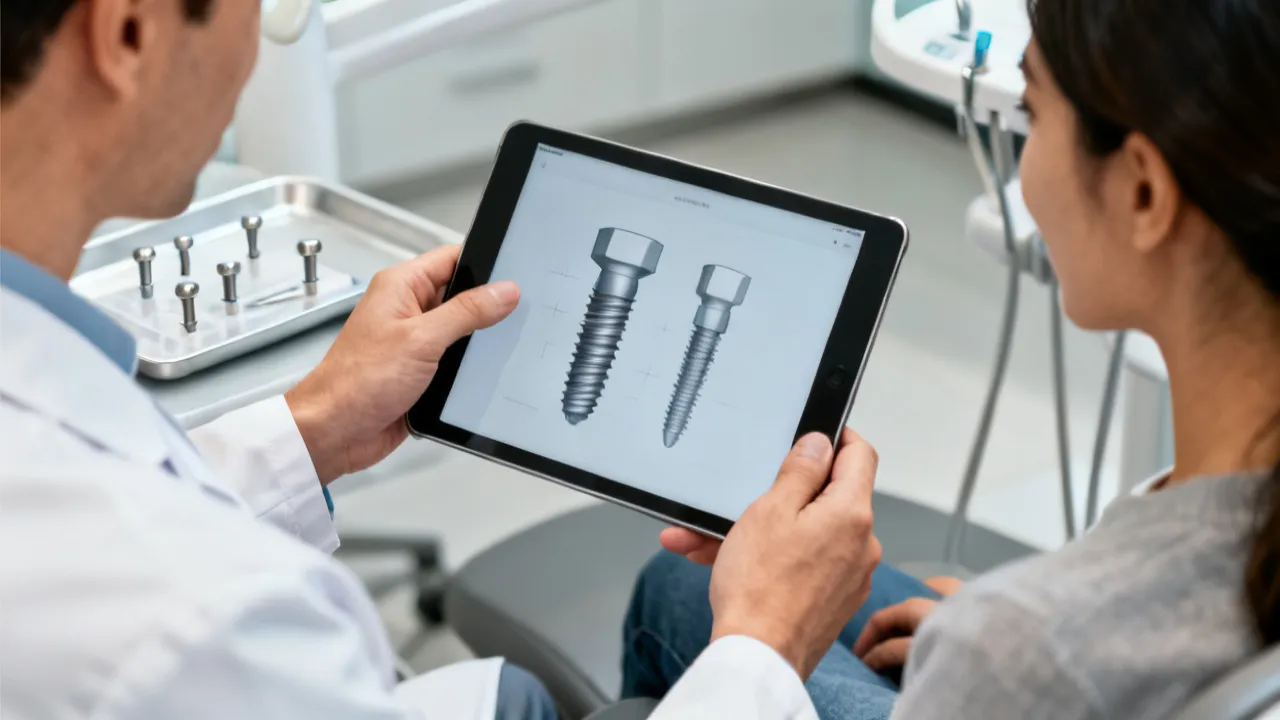
PMOC Abrava is often approached as a clinically relevant dental product or component category where real-world success depends less on marketing language and more on process control—from specification and documentation to installation, maintenance, and follow-up protocols. In procurement and clinical operations, the difference between “it should work” and “it works reliably every time” usually comes from how well an item is defined, tracked, and handled across the supply and clinical chain. Because “PMOC Abrava” may be used in different supply contexts (for example, as a named material/product within a catalog, a branded part, or a shorthand term in procurement communications), the most responsible way to evaluate it is to confirm the exact composition, intended application, compliance documentation, and item identity before any procurement or clinical use.
In modern dentistry, procurement decisions rarely hinge on a single line-item description. Instead, expert teams typically review traceability (lot numbers and batch documentation), handling requirements, compatibility with existing systems, and service capability for logistics and technical support. For PMOC Abrava, those same diligence steps apply—especially if you are selecting it for patient-facing workflows, where reproducibility, traceability, and documentation completeness are not optional.
Equally important, clinics must recognize that product names and labels can vary across suppliers, distributors, and internal systems. “PMOC Abrava” might reference an OEM part, a distributor’s internal catalog label, or a bundled item that includes multiple subcomponents. Therefore, any clinic evaluating PMOC Abrava should treat the term as a starting identifier and then verify the full technical and regulatory details that correspond to your specific intended use.
Within dental product selection, the core question is always: “Does this item reliably perform in the environment it will face?” For PMOC Abrava, clinicians and procurement teams often connect evaluation to multiple factors that extend well beyond the initial purchase price. In practice, they evaluate:
When PMOC Abrava is integrated into a clinical workflow—whether as a component, a part of a broader procedure, or a material involved in treatment steps—the performance you experience is influenced by how the product is prepared, stored, applied, and documented.
Clinicians and procurement teams typically connect the evaluation to:
From an industry standpoint, the strongest predictor of consistency is rarely the product name; it is the completeness of the documentation package and the clarity of workflow instructions. When “PMOC Abrava” is treated as a label rather than a controlled specification, clinics may run into issues such as wrong version selection, incomplete documentation, or incompatible packaging that complicates receiving and storage. That is why a buyer should not treat the term as self-validating. Instead, they should treat it as a pointer to the exact SKU/specification and documentation package that matches your use case.
Clinically, the consequences of weak selection processes can be cumulative. Even small variations—such as using a slightly different material grade, failing to store under the correct conditions, or applying an item with the wrong handling approach—can increase uncertainty. That uncertainty can later manifest as inconsistent results, extra chair time, delays while troubleshooting, or administrative burden when batches need to be identified for compliance purposes.
When you search for “PMOC Abrava,” you may encounter varying pricing depending on the channel (direct supplier versus distributor), packaging size, certification scope, lead time, and whether value-added services are included. Those services might include technical documentation, installation support, onboarding, training, or enhanced traceability records that make internal audits easier.
Important objective approach: if you are comparing price points, compare on a like-for-like basis. For example, compare the same specification, packaging configuration, and documentation level (including traceability and certificates). Without that discipline, lower cost can conceal higher total costs—delays due to missing paperwork, additional administrative steps, rework caused by nonconformity, or troubleshooting time if compatibility expectations were not aligned.
In procurement practice, cost is not only the purchase price; it is also the operational effort required to receive, verify, store, document, and support the item through its lifecycle. If PMOC Abrava is used in a high-throughput environment, even minor friction in receiving or documentation can affect schedule utilization and staffing. Therefore, clinics should treat price comparisons as “total package comparisons,” not just unit pricing comparisons.
Similarly, supplier selection matters. Clinics and procurement teams frequently evaluate:
Because you requested localization rules—replacing city/country placeholders with “nearby”—any location-specific terms embedded in source data should be generalized as “nearby”. In practical terms, it means evaluating whether local or regional suppliers can consistently meet your lead-time and documentation requirements. “Nearby” can be helpful for delivery speed and communication coordination, but it should never replace due diligence. A supplier that delivers quickly can still provide incomplete documentation, inconsistent labeling, or insufficient support when there is a compatibility question.
To evaluate “nearby” suppliers responsibly, clinics should ask additional questions related to supply continuity: What is the lead time under typical conditions and during busy periods? What happens if documentation is delayed? How are returns handled if a batch is found to be nonconforming? If a clinic is part of a larger corporate structure, they should also confirm whether there are internal procurement constraints or preferred supplier frameworks that impact which PMOC Abrava definitions are acceptable.
Experienced professionals tend to follow a repeatable logic: identify the exact specification, verify compliance documentation, confirm compatibility, then evaluate total cost of ownership (TCO) and lifecycle support. The “expert” advantage is not memorizing product facts; it is resisting shortcuts—especially when product naming can vary across catalogs, distributors, and internal procurement systems.
Below are decision points that often separate smooth deployments from problematic ones:
In practice, the most preventable failures typically occur in the early phases of selection and receiving. For example, a clinic may receive an item that matches the “general concept” of PMOC Abrava but differs in version, packaging format, or documentation scope. Another common failure is assuming that a supplier label implies a certain specification, rather than verifying it through datasheets or certificates. Experts treat those risks as process issues that can be controlled through standard checks.
Clinically, it is also helpful to anticipate how PMOC Abrava will be used over time. If the product’s behavior changes based on storage temperature, humidity, or sterilization conditions (where applicable), then procurement planning must include appropriate storage setups and staff routines. If your clinic lacks the conditions needed to maintain proper storage, no amount of supplier documentation will fully compensate; the clinic must be ready to follow the documented requirements.
Dental products and components typically fall under quality management expectations and regulatory oversight that emphasize patient safety, traceability, and controlled manufacturing. Even when a product is suitable in concept, clinics must still ensure that procurement and use follow documented requirements. The regulatory “shape” varies by jurisdiction and product classification, but the underlying quality logic is consistent: products must be identifiable, supply chains must be controlled, and records must allow investigation when issues occur.
For objective grounding, quality management principles commonly referenced across medical product supply include those articulated in international standards. For example, organizations often align supplier quality with ISO 13485 (quality management systems for medical devices). Clinics and procurement teams may also reference broader expectations for risk management and documentation controls consistent with recognized medical quality practices.
In addition, dental and medical procurement commonly reflects guidance that encourages maintaining records, verifying product identity, and ensuring staff follow defined handling and usage instructions.
Reliable reference sources:
It is also important to clarify an operational point: referencing standards does not automatically guarantee a specific product’s performance. Instead, it sets expectations for how quality should be managed—how suppliers validate processes, how clinics verify incoming materials, and how both parties maintain records. Clinics should therefore use standards as a framework for due diligence rather than as a substitute for verifying the specific PMOC Abrava item you are buying.
The following table supplements “additional important information” by organizing buyer due diligence into a practical comparison format. No hyperlinks are included, per your requirement.
| Evaluation Area | What to Ask/Verify | Why It Matters Clinically | Acceptable Evidence |
|---|---|---|---|
| Product Identity | Does “PMOC Abrava” map to a specific SKU/specification intended for your use case? | Prevents accidental substitution and workflow mismatch | Exact catalog description, technical datasheet, intended use statement |
| Traceability | Can the supplier provide batch/lot traceability details? | Supports complaint investigation and accountability | Lot/batch numbers, traceability records, batch documentation |
| Quality Documentation | Are certificates and quality records provided for each shipment? | Reduces the chance of nonconformity | Certificates of conformity, documentation package completeness |
| Compatibility | Does PMOC Abrava integrate with your current system/workflow? | Minimizes variability and prevents rework | Compatibility notes, workflow guidance, handling instructions |
| Handling & Storage | What are the storage conditions and handling rules? | Prevents degradation and operational errors | Storage conditions, shelf-life guidance, sealed packaging expectations |
| Supplier Capability | Can they respond quickly to technical questions or issues? | Improves continuity during busy clinical schedules | Defined support process, complaint handling terms, documentation responsiveness |
| Total Cost | Does the quoted price reflect required documentation and lead-time expectations? | Avoids hidden costs in admin, delays, and replacements | Clear quotation breakdown, service inclusion clarity |
To make this table truly operational, clinics often convert it into internal checklists. For example, a receiving staff member can use the “Traceability” and “Quality Documentation” rows as a gate before the item enters storage. Similarly, the “Handling & Storage” row can prompt a quick scan of storage readiness: do you have the correct storage temperature range (if applicable), do labels remain readable, and do you have a system to track batch placement and usage?
This section provides a step-by-step guide (with objective conditions/requirements) that clinics and procurement teams can use when assessing PMOC Abrava in practice. The goal is not to create a heavy bureaucracy; the goal is to create enough control so that each batch entering clinical workflow is the right one, in the right condition, with the right documentation, and with staff able to apply it consistently.
Because your selection impacts patient-facing clinical workflows, due diligence should be informed by recognized medical quality and risk principles. ISO 13485 and quality system expectations provide a general framework for documenting and controlling supplier quality, while regulators (for example, U.S. FDA quality system concepts) emphasize consistent verification, traceability, and recordkeeping. These references do not validate a specific product’s performance. Instead, they support how organizations should manage quality and compliance responsibilities through controlled processes.
Clinics can translate these high-level concepts into practical routines: define the item precisely, verify incoming identity, store appropriately, use per documented instructions, track usage by batch, and handle deviations through a defined escalation path. Those routines are the operational “bridge” between standards and patient safety.
Operationally, clinics often find it useful to assign roles and responsibilities. For example, procurement verifies the order matches the specified PMOC Abrava identity; receiving staff verifies lot numbers and packaging condition; clinical lead confirms compatibility and instructs staff; quality/compliance personnel ensure records can be retrieved by batch if needed.
In real clinics, procurement and clinical use are tightly connected. Even if PMOC Abrava is “approved” in a general sense, the day-to-day implications depend on how it is integrated. From an expert lens, the item becomes part of a chain: patient consultation → planning → preparation → controlled receiving → proper handling → procedural steps → post-procedure monitoring → documentation.
That means the “quality” you experience is often a function of process discipline. When the chain is well-controlled, staff rely on documented steps and the clinic can trace what was used in each patient case. When the chain is weak, variability increases and the clinic becomes dependent on memory or informal checks—both of which are not reliable under busy schedules.
From a practical perspective, the steps where issues tend to originate include:
Clinics also need to think about how PMOC Abrava interacts with documentation systems. For batch-traceable items, clinics often maintain internal mapping between: (1) the batch/lot used, (2) the date/time the item entered clinical workflow, and (3) the procedure or patient encounter. The internal system must be able to answer, quickly and accurately, “Which batch did we use?” and “What should we do if a complaint is raised?”
When clinics fail to build this mapping early, they may discover too late that they cannot reconstruct the required information. That can delay investigations and complicate compliance obligations. Therefore, integrating PMOC Abrava into day-to-day workflow includes both clinical steps and administrative traceability steps.
Many buyers discover that supplier quality is not identical to supplier convenience. A reliable channel is one that can provide answers in a standardized format: clear product identity, documentation aligned with the intended use, and a predictable process for procurement resolution when issues occur.
From an industry standpoint, buyers frequently evaluate whether the supplier:
When price comparisons show large gaps, the expert reaction is to ask: “What’s missing?” The missing element is often documentation scope, shipping conditions discipline, batch-level traceability coverage, or the inclusion of required receiving/quality support materials—not necessarily the core item itself.
To operationalize this, clinics can request a “documentation checklist” from the supplier. For example, they can ask: What certificates are provided? Does each shipment include batch numbers? Is there an intended-use statement? Are storage conditions included? Is there a procedure for complaints? Asking these questions early prevents time-consuming back-and-forth after the first delivery.
In addition, reliable channels tend to support staff training and onboarding. If PMOC Abrava use requires specific application steps or careful handling, then supplier guidance reduces the learning curve. It also helps ensure that staff apply the item as intended, rather than relying on assumptions based on prior experiences with different brands or versions.
PMOC Abrava is commonly used as an identifier for a specific dental product category, component, or catalog item within supplier documentation. Because naming can vary by supplier, you should confirm the exact SKU/specification, intended use, and documentation scope associated with the identifier before procurement. In other words: verify what “PMOC Abrava” means in concrete terms (part number, material description, intended application), not only as a label.
Clinics should evaluate product identity clarity, traceability (lot/batch documentation), handling and storage requirements, compatibility with existing workflows, and supplier responsiveness. Total cost of ownership can be higher for low-cost offers if they require additional administrative steps, create delays, or increase variability due to insufficient guidance or unclear documentation.
Beyond that, clinics should also evaluate how quickly the supplier can correct documentation errors and whether the supplier supports root-cause investigations if a batch-related issue occurs. A low purchase price is not a meaningful advantage if the clinic lacks the documentation necessary to manage risk.
Request an intended-use statement, handling/storage instructions, datasheet/specification confirmation, and batch/lot traceability documentation. If quality certificates are available for the shipment, those should also be included in the receiving package. Ideally, the documentation should map clearly to the batch/lot number on the shipment labeling, so that internal records can be reconciled without ambiguity.
If the supplier uses an e-document delivery method, clinics should confirm whether electronic documents are acceptable under their internal compliance framework and whether they are available immediately or only after dispatch. Clinics should avoid situations where the item arrives but key documentation arrives later without clear accountability.
Yes. A controlled receiving process typically includes verifying product identity, checking packaging integrity, confirming lot/batch numbers, and ensuring documentation completeness. Staff should then follow the supplier’s handling guidance to maintain consistency. If anything is missing or unclear, the item should be quarantined and not used until resolved.
Practical receiving controls may include: checking that labels are legible, verifying expiry or shelf-life information if present, confirming that packaging was not damaged in transit, and ensuring that documentation references the same batch/lot identifiers that are physically present on the shipment.
Document the discrepancy (product identity details, lot number, packaging condition, and any missing documents). Then follow the supplier’s defined complaint or return process. Maintain internal records so issues can be linked to specific batches. If patient-impact is possible, clinics should involve internal compliance and clinical leadership according to their established procedures.
From a quality control perspective, the key is to preserve evidence and ensure traceability. Do not discard packaging or labels. Take photos if that aligns with your internal policies, record timestamps, and ensure the issue is connected to the batch used or received.
Compare like-for-like items: the same specification and documentation package. Evaluate lead times, logistics discipline, response quality to technical questions, and clarity of replacement/complaint handling. Price alone is insufficient.
For an objective comparison, clinics can use a structured scoring approach: documentation completeness score, traceability support score, compatibility clarity score, and responsiveness score. The supplier with the best documentation and support is often the one that minimizes operational risk and reduces time spent troubleshooting.
If a supplier is located “nearby,” it may help with lead-time and shipping coordination. However, an expert approach still requires the same documentation and quality checks as with any supplier. Local delivery does not replace due diligence; instead, it can reduce delays while still requiring verification.
Clinics can also evaluate whether the supplier’s “nearby” logistics capability includes consistent temperature or handling controls if the product has storage constraints. Even for products where temperature is not a primary constraint, packaging integrity and label readability remain crucial.
PMOC Abrava should be understood through a process-first mindset: confirm exact identity and specification, validate documentation and traceability, verify workflow compatibility, and apply controlled receiving and handling. In dentistry, consistent outcomes come from disciplined quality management rather than assumptions based on product names or isolated price points.
If you are currently evaluating PMOC Abrava for procurement or integration into a clinical workflow, start by requesting a complete documentation package and clarifying compatibility. Then compare suppliers using like-for-like details, focusing on traceability, handling requirements, and reliable technical support. That approach is the objective path to safer, more consistent utilization—where outcomes are ultimately shaped by how well the entire chain is managed, from supplier documentation to day-to-day clinical application.
Ultimately, a clinic’s best advantage is not simply choosing PMOC Abrava; it is choosing how PMOC Abrava will be governed inside the clinic. When the clinic sets clear receiving gates, trains staff consistently, tracks batches, and maintains a defined escalation path, it converts product selection into predictable clinical operations. That is what buyers and clinics need to know first.
If you want, share the exact context in which you see “PMOC Abrava” (for example: catalog listing, distributor label, or internal code) and what kind of documentation you already receive. Then the due diligence questions above can be turned into a targeted checklist for your specific workflow and compliance expectations.
Striking the Perfect Balance: Navigating Premiums and Out-of-Pocket Expenses in Senior Insurance Plans

Explore the Tranquil Bliss of Idyllic Rural Retreats

How to Make Lasting Memories at Disneyland Attractions

Affordable Phones and Plans for Seniors

Affordable Full Mouth Dental Implants Near You
Unlock the Top Kept Secrets to Finding Your Ideal Dentist for Flawless Dental Implant Results!

Discovering Springdale Estates

Unveiling RS Sul Telecom Services

The Guide to Car Trading

Understanding PMOC Abrava in Modern Dentistry
This guide explains PMOC Abrava with an objective, clinician-focused overview of what it is, how it is planned, and what buyers typically evaluate when selecting products or services. Background information covers common clinical workflows, supplier considerations, and practical conditions for safe, consistent outcomes across dental-grade materials and treatment planning.
